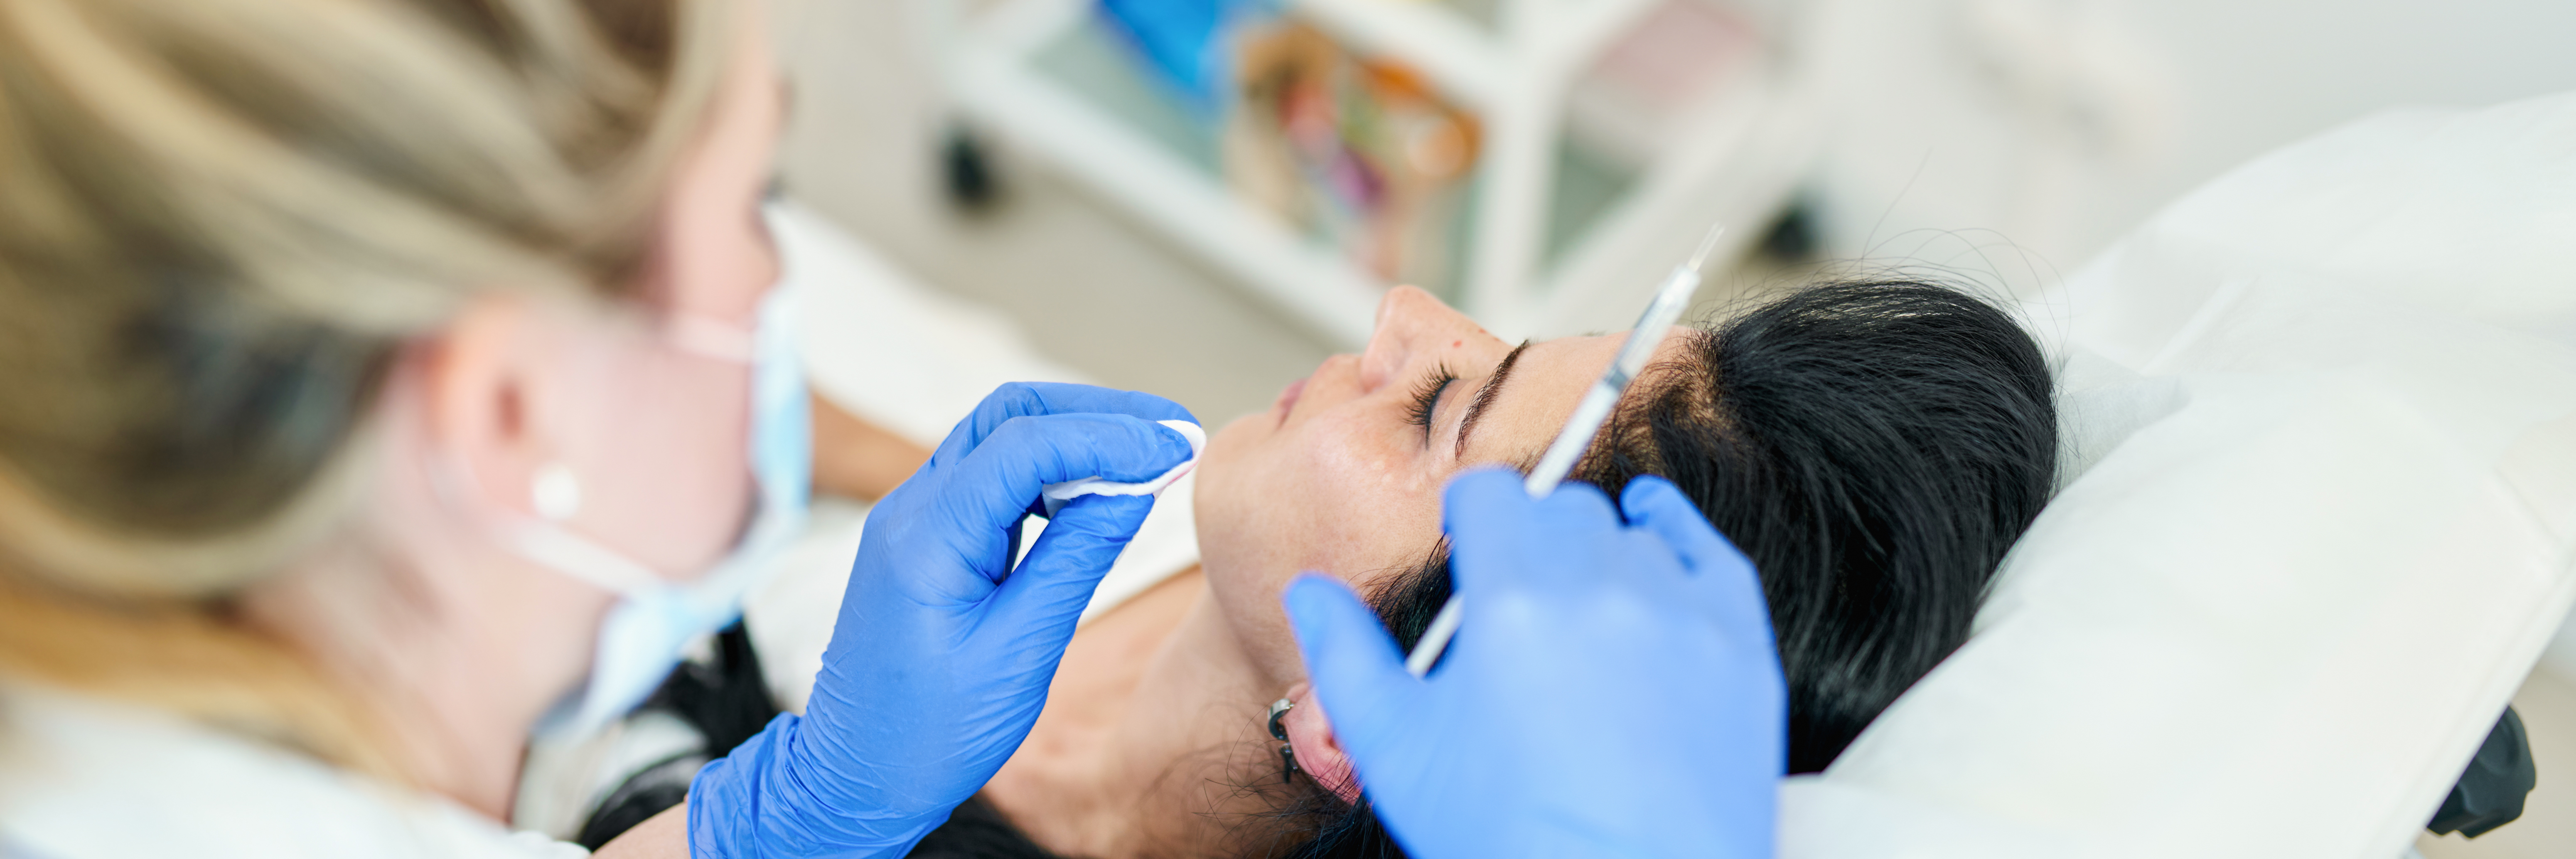
Ophthalmology and aesthetics have been closely linked since the sector’s earliest days. The cosmetic use of botulinum toxin was famously pioneered by ophthalmologist Dr Jean Carruthers and her dermatologist husband, Dr Alastair Carruthers, after patients receiving treatment for eye muscle disorders noticed an improvement in facial lines.
Today, the periorbital area, the region around the eyes, remains one of the most requested treatment zones in aesthetics. The delicate eye area is often the first feature to show the signs of ageing, with patients seeking treatment for a range of concerns from crow’s feet, under-eye hollows, dark circles, pigmentation, skin laxity, puffiness, or changes in skin quality.
Alongside established treatments such as botulinum toxin and dermal fillers, practitioners are also seeing growing interest in regenerative treatments, including polynucleotide and energy-based approaches. More recently, treatments for dry eye have emerged alongside cosmetic indications, making the eye area an even more prominent topic of conversation, particularly when it comes to women’s health and menopause, where dry eye is a major concern.
But this is also a complex area to treat. Complications can be life-changing and permanent, ranging from temporary swelling and asymmetry to problems affecting eyelid function, the ocular surface, and, in rare cases, vision impairment as a result of vascular occlusion. Understanding the specific anatomy and risks of the eye area is therefore central to safe practice.
The anatomy around the eye leaves little room for error. A dense network of blood vessels surrounds the orbit, with connections between branches of the facial circulation and the ophthalmic artery, which supplies structures within the eye. This vascular anatomy is one reason why inadvertent injection of dermal filler into a blood vessel can, in rare cases, have serious consequences.
The skin is also particularly thin and mobile. Small amounts of swelling, product migration, or changes in muscle function may be more visible here than elsewhere on the face. The lower eyelid has limited tolerance for scarring or tissue contraction, while interference with normal eyelid closure can leave the cornea exposed.
There is also the proximity of the globe itself. Lasers, other energy-based devices, chemicals, topical anaesthetics, and treatment products can cause ocular injury if appropriate precautions are not taken. A 2024 review of facial laser and light treatments identified complications including conjunctival burns and other ocular injuries, underlining the importance of treatment-specific eye protection.
Different treatments present different risks, so practitioners need to understand the potential complications associated with each procedure they offer.
Botulinum toxin: Treatment around the glabella, forehead, and lateral eye area can affect nearby muscles if the toxin spreads beyond the intended site. Potential complications include eyelid ptosis, where the upper eyelid droops, brow ptosis, ectropion, where the lower eyelid turns outwards, and lagophthalmos, where the eye cannot close fully. Changes to blinking and eyelid closure can also contribute to dry eye symptoms and corneal exposure. Careful assessment of existing brow and eyelid position before treatment is important, as is early recognition of unexpected visual symptoms or changes in ocular function.
Dermal fillers: The tear trough and nearby areas need advanced anatomical knowledge. Vascular occlusion occurs when blood flow through a vessel becomes blocked. In rare cases, filler entering the arterial circulation can travel through connected vessels towards the ophthalmic circulation, potentially causing retinal artery occlusion and vision loss. Any sudden visual change during or after treatment should be treated as a medical emergency.
Polynucleotides: Polynucleotides have become increasingly popular for periorbital skin quality, fine lines, and dark circles. Published literature suggests potential benefits for skin texture and rejuvenation, but this does not remove the need for careful patient selection and injection technique. The delicate anatomy of the eye area remains the same, and practitioners should consider risks including swelling, bruising, infection, inflammatory reactions, and the consequences of poor injection placement. Particular care may be needed in patients with existing oedema or impaired lymphatic drainage, as post-treatment swelling can be more pronounced. Vascular occlusion is still a possibility although less likely than with dermal fillers.
Plasma fibroblast treatments: Treatments designed to create controlled thermal injury and tissue contraction can cause burns, pigment changes, scarring, and problems with eyelid position. The lower lid needs particular caution because excessive contraction or scarring may contribute to ectropion. Risk is not limited to the device itself. A published case report described bilateral chemical eye injury after topical anaesthetic cream entered both eyes before plasma fibroblast treatment.
Thread lifting: Thread placement near the temporal and periorbital region needs a clear understanding of tissue planes and nearby nerve and vascular structures. Incorrect placement can lead to visible or palpable threads, dimpling, asymmetry, pain, and other complications. Practitioners should be cautious about extending thread techniques towards the eye area without dedicated training.
Chemical peels and topical treatments: Chemical ingress into the eye can cause significant injury. Product choice, application technique, positioning, appropriate eye protection, and immediate access to irrigation should all form part of the treatment protocol. Practitioners also need to consider how topical anaesthetics and other products used before a procedure could migrate into the eye.
The relationship between aesthetics and ophthalmology is developing further as interest grows in treatments that address both appearance and ocular comfort.
Dry eye disease, for example, is increasingly discussed in aesthetic settings. It can be linked to a range of factors, including age, hormonal change, contact lens use, screen exposure, and meibomian gland dysfunction. The meibomian glands sit within the eyelids and produce oils that help stop tears evaporating too quickly.
Research has explored the use of intense pulsed light and heat-based technologies for some forms of dry eye disease, particularly where meibomian gland dysfunction is involved. There has even been the emergence of filler therapy for dry eye where a canalicular gel is injected directly into the tear ducts to block drainage and help the eyes retain natural tears for longer.
This is an important development, but it also raises questions about scope of practice. Treating a diagnosed eye condition is different from carrying out a cosmetic skin treatment around the eyes. Practitioners considering this area need suitable training, a clear understanding of their professional boundaries, appropriate patient assessment, and established referral pathways.
Safe periorbital treatment starts before the procedure itself. A thorough medical history should explore previous eye surgery, visual problems, dry eye symptoms, contact lens use, previous aesthetic procedures, allergies, relevant medicines, and anticoagulant use. Practitioners should also ask about previous complications and assess existing asymmetry, brow position, eyelid closure, swelling, and skin quality.
Good practice includes:
Consent should be specific to the treatment and the individual patient. A generic form is no substitute for a documented discussion about material risks, alternatives, expected outcomes, and the particular considerations that apply around the eyes.
A complication plan should be in place before treatment starts. Practitioners need to know which symptoms they can manage within their competence and which need urgent escalation.
Blanching, unusual or escalating pain, mottled skin, or other signs of vascular compromise after filler treatment need immediate assessment. Any change in vision, including blurred vision, loss of vision, double vision, or a visual field disturbance, should be treated as an emergency and trigger urgent escalation through the clinic’s established pathway.
Ptosis after botulinum toxin may be temporary, but practitioners should assess its severity and distinguish a recognised treatment complication from symptoms that could indicate another neurological or ophthalmic problem. Patients with eye pain, significant redness, new visual disturbance, or difficulty closing the eye may need urgent specialist assessment.
Burns and tissue injury after lasers, plasma treatments, chemical peels, or other energy-based procedures also need a clear first-aid and escalation plan. Where the eye itself may have been exposed or injured, prompt ophthalmic assessment is important.
Every decision should be documented clearly, including symptoms reported, examination findings, advice given, photographs where appropriate, treatment provided, referrals made, and follow-up arrangements.
General training in injectables or devices does not automatically prepare a practitioner for every treatment around the eyes. The periorbital area needs specific study of its anatomy, treatment-related risks, patient selection, complication recognition, and emergency management.
Clinic owners also have a role to play. Governance should cover who is trained to carry out each treatment, how competence is assessed, what emergency equipment and medicines are available, and how staff escalate concerns. Referral pathways should be established before they are needed, rather than improvised during a complication.
Practitioners should also check that any new treatment is within their scope of practice and covered by their insurance before adding it to the clinic menu. Read our related guide to insurance risks in ocular aesthetics for more on liability, policy cover, and claims considerations.
The eye area can offer high levels of patient satisfaction, but it needs careful assessment and a clear understanding of the risks involved. As the range of periorbital treatments grows, and the boundaries between aesthetics, regenerative medicine, and ocular health continue to overlap, practitioners need to look beyond the treatment technique alone.
Strong anatomical knowledge, appropriate training, careful patient selection, clear consent, detailed records, and a rehearsed complication plan, all help to protect patients. In an area where small changes can have a significant impact on appearance and function, preparation matters.
Complications can lead to complaints and claims. To discover how Hamilton Fraser can support you, call us on 0800 63 43 881 or get an online quote today..